Tailoring Pulmonary Rehab to Close the COPD Gap, With Omid Pourshahid, MD - HCPLive
This story deserves to be shared
Send it to someone who'd care, or post it on your networks.
At CHEST 2026, Pourshahid argued for matching patients to center-based, hybrid, or virtual pulmonary rehab based on a structured assessment. Arguing the pro side of a debate at the American College of Chest Physicians (CHEST) 2026 Annual Meeting in Phoenix, Omid Pourshahid, MD, MPH, FCCP, Medical Director, Pulmonary Rehabilitation, Temple University Hospital, said pulmonary rehabilitation should be tailored to each patient’s clinical status and barriers to care rather than delivered through a single center-based model.¹The position builds on a long-standing gap in pulmonary rehabilitation uptake. In a retrospective cohort of 197,376 Medicare beneficiaries hospitalized for COPD in 2014, only 2721 (1.5%) initiated pulmonary rehabilitation within 90 days of discharge.² Initiation within the 90-day window was associated with a lower risk of death at 1 year (hazard ratio [HR], 0.63; 95% CI, 0.57-0.69; P <.001).
This article is an excerpt. To read the full content, visit the original source. HCPLive
Related articles
Three Ways a Pulmonary Fibrosis Lung Health Navigator Can Support You - American Lung Association
Bilateral Sensorineural Hearing Loss as the Sentinel Presentation of Granulomatosis With Polyangiitis - Cureus
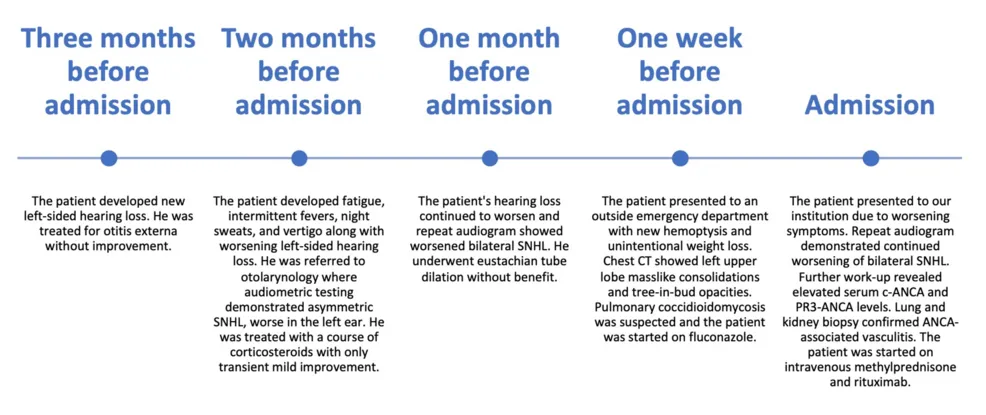
Granulomatosis with polyangiitis (GPA) is a systemic necrotizing granulomatous vasculitis classically involving the upper and lower respiratory tracts and kidneys. Timely diagnosis requires a high index of suspicion for the presenting symptoms. Otolaryngologic manifestations are commonly reported but most often involve the nasal and paranasal sinuses. Sensorineural hearing loss (SNHL) as the sole initial manifestation of GPA is uncommon and may contribute to diagnostic delay. We report a case of a 67-year-old male who presented with rapidly progressive bilateral SNHL that preceded pulmonary and renal manifestations by several months, during which the patient was treated for otitis externa and Eustachian tube dysfunction without improvement. Development of pulmonary symptoms prompted additional workup, which demonstrated markedly elevated cytoplasmic anti-neutrophil cytoplasmic antibody (c-ANCA) and proteinase 3-anti-neutrophil cytoplasmic antibody (PR3-ANCA), raising concern for GPA. Histopathology then confirmed the diagnosis. The patient was treated with high-dose corticosteroids and rituximab with serologic remission; however, his hearing loss was largely irreversible. This case
0 comments
No comments yet. Be the first to share your thoughts!