A health-system-scale, episode-resolved multimodal atlas of cancer cachexia - Nature
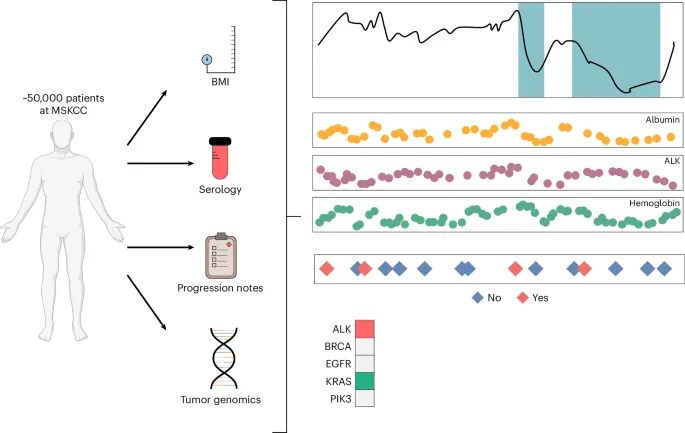
MainThe uncontrolled cellular growth and local tissue disruption produced by tumorigenesis elicit a complex host response, including chronic inflammation, metabolic reprogramming and endocrine dysfunction1,2. These systemic changes can emerge early and persist throughout the disease course, contributing to profound alterations in appetite, energy balance, tissue composition and immune function3,4. Together, they underlie debilitating syndromes such as fatigue, anorexia and cachexia. Understanding these pathophysiologies in human patients with cancer requires integrated, longitudinal measurements of host physiology and tumor biology. Cancer cachexia (herein, ‘cachexia’) is a paraneoplastic metabolic syndrome characterized by progressive, unintentional weight loss3,5,6 accompanied by muscle wasting7 that affects approximately half of all patients with cancer3,8. Cachexia is associated with reduced quality of life9,10, premature termination of therapy, increased treatment complications and elevated risk of death11,12,13. Despite its prevalence and well-acknowledged consequences for morbidity and mortality, the underlying causes of cachexia are poorly understood.
This article is an excerpt. To read the full content, visit the original source. Nature
Related articles
Multimodal AI refines EAU risk stratification in patients undergoing radiotherapy for prostate cancer - Nature
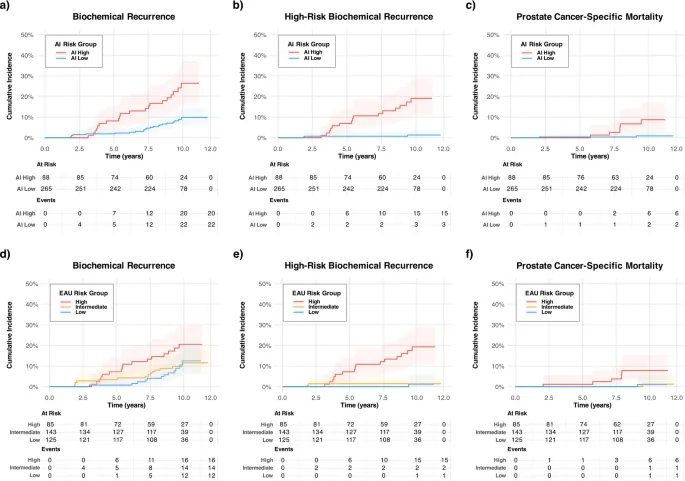
IntroductionRisk stratification before definitive treatment is fundamental to prostate cancer management, guiding treatment intensity and patient counseling. The European Association of Urology (EAU) risk classification system, based on prostate-specific antigen (PSA), International Society of Urological Pathology (ISUP) grade group, and clinical stage, remains the cornerstone for treatment decision-making in patients undergoing radiotherapy (RT)1. Despite their clinical utility, outcome heterogeneity remains substantial. In a Swedish population-based cohort of patients treated with RT, the 15-year cumulative incidence of biochemical recurrence (BCR) ranged from 18% in EAU low-risk disease to 36% in EAU high-risk disease, indicating that currently used categories do not fully capture individual prognosis2. Improving pre-treatment prognostic stratification may therefore help identify clinically distinct subgroups within established categories.
0 comments
No comments yet. Be the first to share your thoughts!